
Season 7
In this episode, Jean-Claude Saghbini, Chief Technology Officer and President of Technology Services at Lumeris, explores how agentic AI can help address healthcare’s primary care access challenge. He argues that incremental efficiencies are not enough; AI must enable the existing clinical workforce to serve more patients and extend care between visits.
Jean-Claude discusses Tom, Lumeris’ AI-powered primary care team member and operating system, which uses patient data to identify next actions and proactively engage patients. He emphasizes that deploying Agentic AI responsibly requires clear guidelines for what AI should do and guardrails for what it cannot do.
Jean-Claude argues that AI models themselves will not create competitive advantage. Differentiation will come from data, domain knowledge, applications, and redesigned workflows. He advises healthcare technology leaders to move beyond the automation, pilot, and perfection traps and make focused enterprise AI investments. Take a listen.
About Our Guest
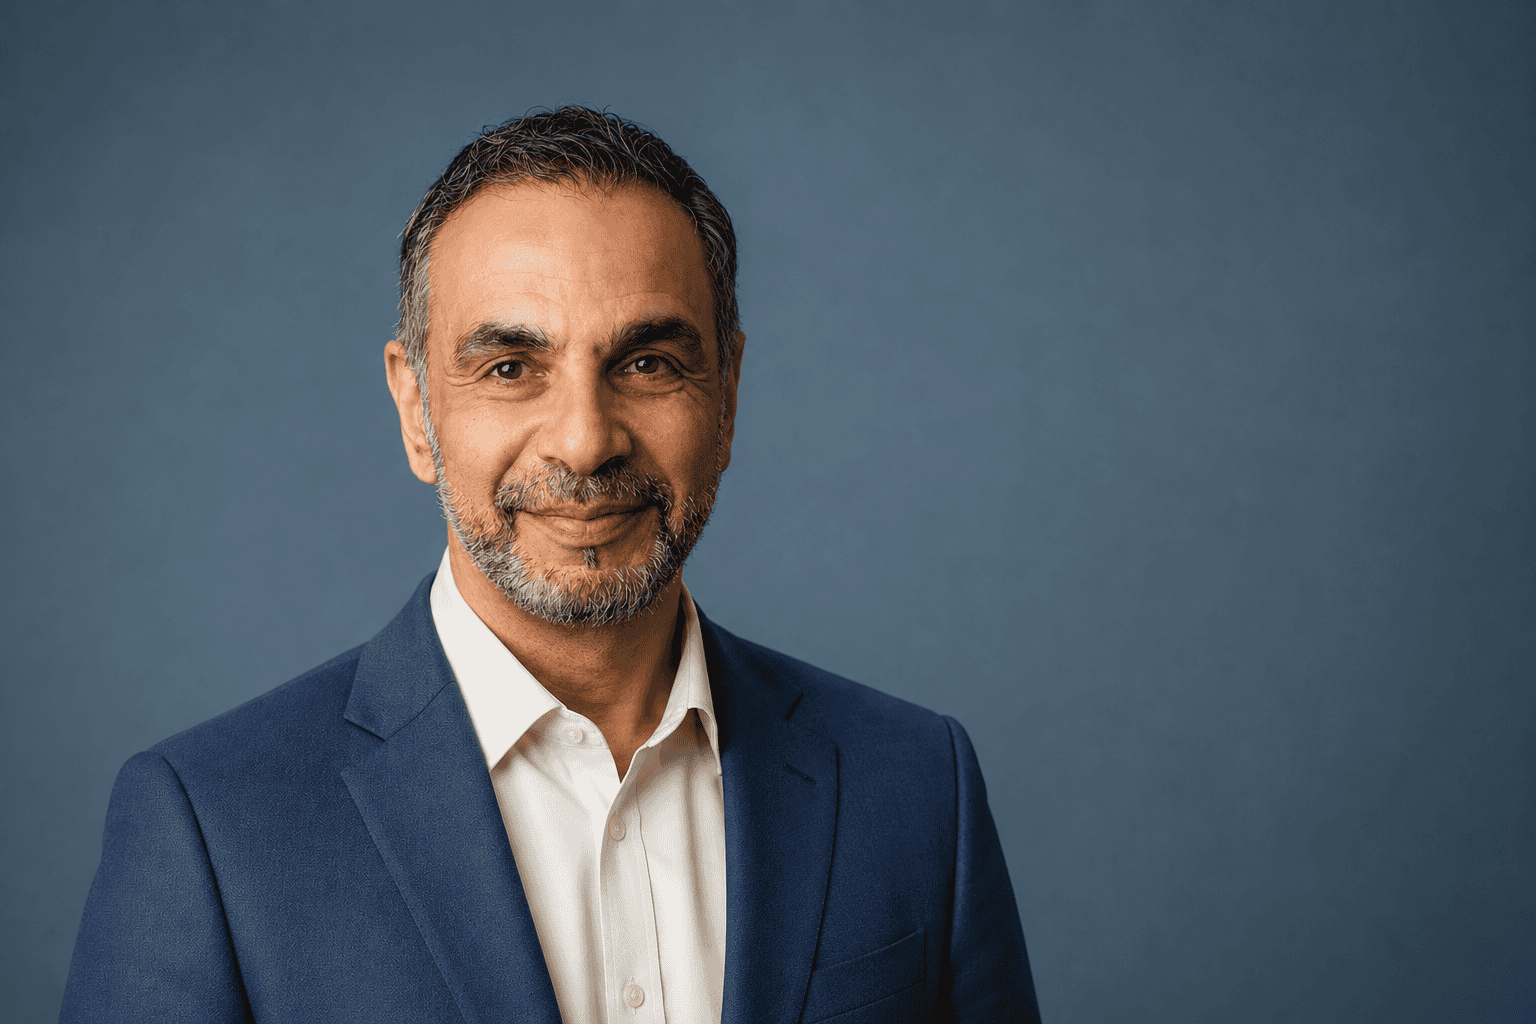
Jean-Claude Saghbini is the Chief Technology Officer and President of Technology Services at Lumeris, where he integrates technological innovations, clinical processes, and operational excellence into leading value-based care solutions. He also oversees the efficient deployment of cutting-edge technologies like Generative AI to ensure optimal healthcare outcomes and client satisfaction.
With two decades of technology and healthcare experience, Jean-Claude is dedicated to seamlessly integrating technology into clinical workflows to improve outcomes and reduce care variability and costs. Previously, he held key leadership roles at Wolters Kluwer Health and Cardinal Health, driving AI innovation, clinical decision support, and pioneering RFID solutions for medical device tracking. Jean-Claude holds a Master of Science in Engineering and Management from MIT Sloan School of Management, as well as a Master of Science degree and a bachelor’s degree in mechanical engineering from MIT and the University of Massachusetts, Dartmouth, respectively. He is also a holder of multiple patents in healthcare technology.
Recent Episodes
Ritu: Hello, listeners. Welcome to Season Seven of the Big Unlock Podcast. My name is Ritu Uberoy, and I’m managing partner at Damo Consulting and your host today. We are welcoming Jean-Claude Saghbini to our podcast. He’s the Chief Technology Officer at Lumeris, where he integrates technological innovations, clinical processes, and operational excellence into leading value-based care solutions. Prior to Lumeris, he has held senior technology leadership roles at Wolters Kluwer Health and Cardinal Health. At Lumeris, JC has been closely involved in developing Tom, the company’s AI-powered primary care as a service platform, and we’re really excited to discuss that today. Welcome to the podcast, JC. Looking forward to an engaging conversation.
Jean-Claude: Absolutely. Thank you for having me. I’m excited.
Ritu: You’ve made the argument that the primary care problem is fundamentally a supply-demand problem, and that adding more digital health applications is not really changing this equation. If AI is going to be different, what exactly needs to change in the operating model? At what point do AI tools stop making physicians ten percent more efficient and actually allow health systems to care meaningfully for more people with the same clinical workforce they have today?
Jean-Claude: Let me unpack that supply-demand problem a bit. Today, about a hundred million people in this country either don’t have access to primary care or have access to extremely inadequate primary care. The reason primary care matters is that it controls about three trillion dollars of spend because it operates so far upstream — and the fact that those people lack access has both healthcare implications for them and significant financial implications at a national level. The primary reason for the gap is actually simple: there are too few primary care physicians in the country to do the work, and that delta continues to grow. In about eight or nine years, we’ll be approaching a shortage of 90,000 primary care physicians. When you look at it that way, tweaking things and applying AI for small efficiencies is not going to work. The problem isn’t at the scale of five or ten percent — it’s at the scale of a hundred million people. So what we want from AI is technology that can bridge that access gap. With the same infrastructure of physicians and clinicians in primary care that we have today, we need to expand access to the hundred million who aren’t getting it — and to the others who are getting primary care, but only whatever time is available to them, not complete primary care.
Ritu: That’s a great perspective, and we’ve been hearing about healthcare deserts — especially with the rural healthcare transformation project. The problem is even more acute in certain areas. We’ve spoken to an ophthalmologist in Alaska where the wait time can be as much as six months. Tell us more about Tom, which is positioned not as a co-pilot but as an AI-powered member of the care team. Tell us about Tom and how it brings in agentic AI to address this problem.
Jean-Claude: We refer to Tom as two things. Tom is an AI primary care team member, and Tom is also an AI primary care operating system — a platform. I’d love to dig into both, but let’s start with value creation. On the value creation side, Tom is an agentic AI primary care team member that effectively becomes part of the care team of a primary care physician. Just as a physician has staff members to help take care of patients, they add one more: Tom. Tom has access to data about the patient, can compute and reason on that data, identify what to do — from closing care gaps to proactive management. This is what we call the BNA, or Best Next Action engine. It determines the best next action for that patient. But more importantly, Tom can act. Tom can act in a conversational way — we use conversational AI through text messages integrated into the workflow, so Tom can proactively engage with patients and effectively manage them in between visits. Between visits there is a desert of information. You leave your physician’s office, and the only thing they know about you next is when you show up again. In that time, nobody knows anything about you. Tom not only brings information about you — it actually helps you manage your medical condition between those visits. That is how we’re able, within a fixed human infrastructure, to use agentic capabilities to manage more interactions with patients and a broader set of patients.
Ritu: Tell us a little more about the OS part that you mentioned.
Jean-Claude: To be able to deliver that, you have to build all of the mechanics underneath. The expression of that delivery might be a conversation Tom has with a patient around a cardiometabolic condition they have. But underneath the cover, we had a bit of an unfair advantage: fifteen years of learnings that Lumeris has accumulated on how to manage patients and populations to better outcomes. We’ve partnered with health systems across the country to do that. We took all of that knowledge and embedded it in the operating system. That gives you components like data ingestion, normalization, and creating a 360-degree view of a patient — whether the data is coming from the EHR, claims, or social determinants of health. We had to build reasoning components that can reason on patients, understand their gaps, and determine what to do about them. We built bidirectional EHR integration — not only to get data from the EHR, but to push data back in. We built patient engagement capabilities: telephony, voice conversational AI, text conversational AI, and a series of agentic services in preventive care, scheduling, chronic condition management, and pre- and post-visit management. We built analytics to surround all of that so you can analyze what’s happening across your population. And last but extremely important — something I’d love to talk more about — we built a safety platform that monitors all of these agents: what they’re doing, tracking clinical metrics, patient sentiment metrics, and objective accomplishment metrics, issuing alerts if things have gone sideways, and ensuring everything stays within the guardrails. The totality of all of that, to us, is Tom.
Ritu: This is really interesting because most of the CIOs we talk to are focused on summarization, documentation, or administrative AI. But you’re saying Tom has agentic capabilities that allow it to make decisions autonomously — some requiring clinician approval, some perhaps not. This raises a lot of questions about trust, governance, and orchestration. How have you approached the trust and governance lens? And when does the human in the loop come into the picture?
Jean-Claude: We use two words internally: guidelines and guardrails, and we live by those. Whenever we build any capability, we define guidelines — what it should do — and then we put the guardrails around what it should not do. We have very strict guardrails: Tom is not a physician, is not a licensed practitioner, and therefore Tom cannot diagnose, treat, or change medications. Those are the guardrails we do not go outside of. Within those guardrails, the guidelines define what Tom can do: engage with patients, check in on them, explain things about conditions, help them manage their condition, check whether they picked up their medication, identify barriers to filling a prescription, connect them back to the care team if gaps are identified, and check on symptoms if a patient expresses them. Those are the guideline capabilities. The guardrails are what we don’t let Tom get out of.
Ritu: Thank you — guidelines and guardrails is a good approach. That leads to the next question: most AI implementations we see have very obvious administrative metrics for ROI. But in this case, where Tom is actually becoming part of the care team, what metrics tell you Tom is improving care and not just creating more interactions?
Jean-Claude: The ultimate metric we look at is access. The definition is straightforward but hard to get to: can the same number of physicians in a health system manage a broader number of patients attributed to primary care? The ROI to the health system is clear — when you have more patients attributed to you, that attribution is monetizable through services the health system provides to that population. The human ROI to patients is that they are now attributed to primary care physicians, whereas otherwise they might wait six or nine months to find one. On the path to those ROIs, there are first-order KPIs along the way: engagement rate between patients and Tom, care gaps that Tom identified and closed, issues patients raised in conversations that Tom connected to the right venue of care, and symptoms that patients expressed that Tom helped direct to the right place. Those are the first-order KPIs. The second-order KPIs are the ROI outcomes I mentioned.
Ritu: That’s a key point — as long as patients are actually getting access to primary care physicians, you can see the system is working. Let’s change tracks a bit. Tell us about your background and how you got into healthcare. We often get very interesting and personal stories from our guests on that question.
Jean-Claude: I’m an engineer, so I’ve spent my career solving problems. Early on I was in horizontal engineering — technologies across the board. At some point I wanted to get into a vertical I felt passionate about. I was looking at renewable energy as one option, and healthcare as the other. I joke that I got into healthcare because I thought it would be easy. I’ve been in healthcare since 2005 — twenty-one years now. I got in on the startup side. I’m in Boston, so we started a company in Concord, Massachusetts. In 2005, we had the ambition of creating a SaaS platform to connect medical device manufacturers and health systems and help manage medical devices via RFID from manufacturing all the way through to implantation in patients. That was my entry into healthcare. The technology was very exciting at the time — RFID was the thing back then, the way AI is now. Now it’s ubiquitous. Back then it was early uses of RFID at national scale. We sold that company — WaveMark — into Cardinal Health. I spent four years at Cardinal Health managing and growing that RFID business from startup scale to enterprise scale. Then I joined Wolters Kluwer Health, where I worked on frontline clinical decision support products like UpToDate, built up the AI Center of Excellence, and did a lot of AI innovation. And this is my third or fourth chapter in healthcare — joining Lumeris about five and a half years ago.
Ritu: Thank you for sharing that story. We have time for one more question. With Tom, you’re bringing together EHR, payer, claims, clinical, and other data to determine the Best Next Action. Do you think the real competitive advantage in healthcare AI will ultimately come from the model — since all we hear about is which model is better or faster — or from the ability to build this longitudinal data and workflow layer?
Jean-Claude: It’s not the models. When any one of the hyperscalers or OpenAI or Anthropic releases a model, eight billion people on the planet have that model the next day. So having that model cannot be a competitive advantage. What I put on my slide — and this comes straight from a conversation with healthcare executives last week — is that the competitive advantage is the data you have. It’s the knowledge you have about care delivery. Many have tried to fix healthcare from a technology lens alone over the past twenty or thirty years, and many have failed doing it purely through tech. So it’s the data and the understanding of patients. It’s understanding the care delivery models and the domain knowledge — whether that’s primary care, surgery, or cardiovascular. And the third element is building actual applications that leverage these highly democratized LLM models, powering them with your data and your understanding of what you’re trying to do, and then integrating them into workflows — and more importantly, creating new workflows. Integrating into existing workflows is a form of automation, and that’s fine. But now we should be able to create entirely new, reimagined workflows. The totality of that — data, domain knowledge, and applications that create new workflows — is what the competitive advantage actually is.
Ritu: That’s a great answer, and it ties back to what you mentioned earlier — Lumeris had all this proprietary data and deep understanding of the problem that you integrated into Tom. Time has flown by and we’re almost at the end. Would you like to share any closing thoughts or advice for listeners in the healthcare technology field?
Jean-Claude: Three pieces of advice that are top of mind for me. First, don’t fall into the automation trap. There’s an urge to automate things because you can see where AI fits and it’s satisfying to do — but you can get stuck there. The bigger opportunity is reimagining new workflows and new ways of delivering value, not just automating existing ones. I see a lot of pure automation of existing workflows right now. You have to do some of that, but at some point you need to invent the new. Second, don’t fall into the pilot trap. Pilots were essential in 2023 and 2024 — you cannot learn this stuff from a textbook, you have to do it. But we are in 2026. If you were still just running pilots, that was the top of the funnel. Now we can narrow the funnel, make big bets, and make those enterprise bets. Third, don’t fall into the perfection trap. LLMs and AI are not perfect, but the problems we’re going after don’t have perfect solutions today either. We can fix enormous problems without perfect AI. The search for perfection will keep technology that patients and clinicians genuinely need locked in a box while we wait for it to be perfect enough to release.
Ritu: That’s great advice. Thank you so much for joining our podcast today. It’s been a wonderful discussion, JC.
Jean-Claude: Absolutely. Thank you so much.
—
Subscribe to our podcast series at www.thebigunlock.com and write us at info@thebigunlock.com
Disclaimer: This Q&A has been derived from the podcast transcript and has been edited for readability and clarity.

Ritu M. Uberoy is a healthcare AI strategist, technology executive, educator, and author dedicated to advancing the responsible adoption of Artificial Intelligence across healthcare delivery, digital health, and life sciences. With more than twenty-five years of leadership experience spanning the United States and India, she is recognized for helping healthcare organizations move beyond experimentation to achieve scalable clinical, operational, and business transformation through AI.
She leads AI innovation initiatives, including the AI Center of Excellence at BigRio, where she works with health systems, healthcare technology companies, and life sciences organizations to operationalize Generative and Agentic AI solutions responsibly. Her work focuses on aligning AI innovation with clinical workflows, governance frameworks, workforce readiness, and patient trust—ensuring technology augments human judgment in high-consequence healthcare environments.
Ritu is the co-author of Generative AI: Unlocking the Next Chapter in Healthcare, a practical guide for healthcare executives navigating enterprise AI adoption. She also hosts The Big Unlock podcast, engaging global healthcare leaders on AI transformation and digital innovation. An active educator and speaker, she conducts executive workshops and participates in global forums like HIMSS, ViVE, Women in Tech, AI-Powered Women, RAISE, and more, shaping the future of AI-driven healthcare. Ritu holds advanced degrees in Computer Science and completed specialized AI programs at Harvard and MIT.

Paddy was the co-author of Healthcare Digital Transformation – How Consumerism, Technology and Pandemic are Accelerating the Future (Taylor & Francis, Aug 2020), along with Edward W. Marx. Paddy was also the author of the best-selling book The Big Unlock – Harnessing Data and Growing Digital Health Businesses in a Value-based Care Era (Archway Publishing, 2017). He was the host of the highly subscribed The Big Unlock podcast on digital transformation in healthcare featuring C-level executives from the healthcare and technology sectors. He was widely published and had a by-lined column in CIO Magazine and other respected industry publications.
Stay informed on the latest in digital health innovation and digital transformation


